Compare Hospital Beds, Motorized ICU Beds & Electro-Hydraulic OT Tables
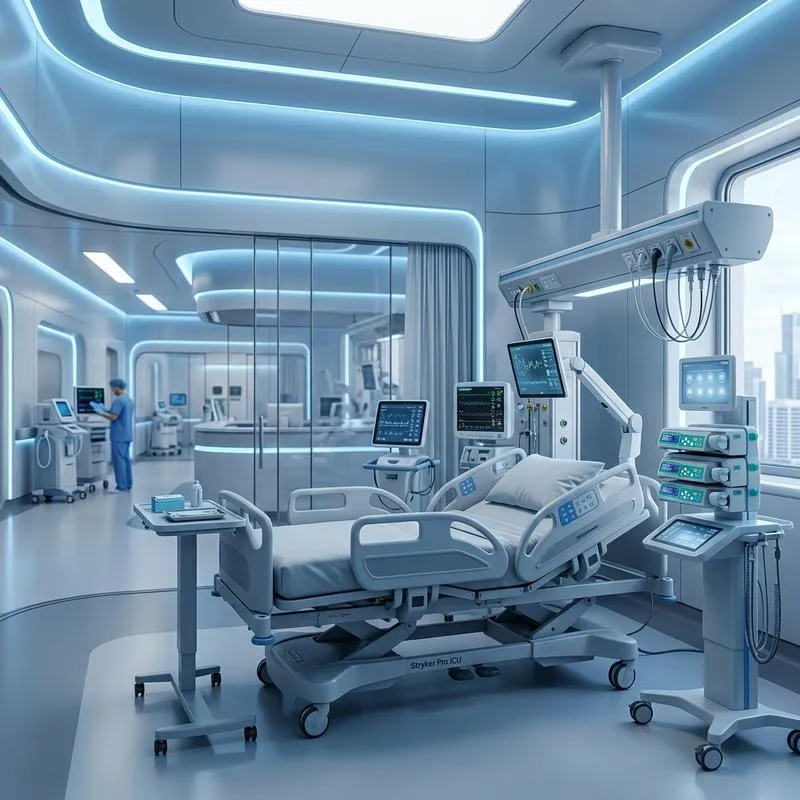
Setting up an intensive care unit (ICU) or expanding critical care bed capacity requires balancing patient clinical safety, nursing ergonomics, and hospital capital expenditure. In India's healthcare infrastructure, an ICU bed is far more than patient furniture—it is an active life-support platform engineered to integrate mechanical ventilators, infusion pumps, patient monitoring arrays, and emergency cardiac arrest defibrillation workflows. Choosing the right bed configuration directly impacts clinical outcomes, preventing pressure ulcers (bedsores), ventilator-associated pneumonia (VAP), and patient falls while facilitating early mobility.
Field Notes from Our Biomedical Engineering Bench
When evaluating ICU hospital beds, hospitals frequently focus solely on the number of motors. However, in our hospital installations across Tier-1 and Tier-2 medical centers, long-term operational success depends on three non-negotiable physical features: (1) Dual CPR release (both instant manual quick-release lever and electronic button), (2) Backrest radiolucency with an integrated X-ray cassette tray to eliminate patient shifting during daily chest radiographs, and (3) IPX4-rated waterproof linear actuators that withstand high-level hospital disinfectant washdowns without actuator burnout.
ICU Bed Price Matrix in India (2026 Procurement Benchmark)
ICU and hospital bed pricing in India is segmented by actuation mechanism (manual crank, semi-electric, vs full motorized), motor engineering (Linak Denmark vs domestic/Taiwanese actuators), and specialized critical care articulation (cardiac chair position, Trendelenburg / Reverse Trendelenburg, and lateral tilt). Below is the wholesale commercial benchmark for institutional procurement:
| Bed Classification | Actuation & Positions | Clinical Ward Application | Ex-Factory Price (INR) | GST Rate |
|---|---|---|---|---|
| Semi-Fowler Bed (Single Crank) | Backrest elevation (0°–75°) via smooth screw mechanism | General wards, recovery rooms, step-down units | ₹14,200 – ₹16,500 | 12% |
| Full Fowler Bed (Dual Crank) | Backrest (0°–75°) & Knee-rest (0°–45°) elevation | Post-op surgical wards, orthopedics, semi-critical care | ₹18,500 – ₹22,500 | 12% |
| 3-Function Motorized ICU Bed | 3 Actuators: Backrest, Knee-rest, Overall Height adjustment | High-dependency units (HDU), neuro step-down, nursing homes | ₹52,000 – ₹68,000 | 12% |
| 5-Function Electric ICU Bed (Full Critical Care) | 4–5 Actuators: Back, Knee, Height, Trendelenburg & Rev-Trendelenburg, Cardiac Chair | Multi-specialty ICUs, CCUs, Trauma centers, Neuro-ICU | ₹92,000 – ₹1,10,000 | 12% |
| Advanced Cardiac Chair ICU Bed with Scale | Full cardiac chair, electronic weighing scale, lateral tilt, Linak motors | Cardiothoracic ICUs (CTVS), ECMO centers, transplant units | ₹1,35,000 – ₹1,85,000 | 12% |
Core Actuation Mechanisms: Manual vs Motorized Comparison
Understanding the structural differences between mechanical and motorized beds helps hospital procurement teams allocate budgets efficiently across general wards, HDUs, and tertiary ICUs.
Manual Crank / Mechanical ICU Beds
- • Mechanism: Concealed stainless steel lead screws with fold-away handles at the foot end.
- • Maintenance: Near-zero electrical dependency; requires periodic lithium-grease lubrication.
- • Limitation: Requires physical effort from nursing staff; height adjustment is either fixed or cumbersome.
- • Best Suited For: Backup beds, Tier-3 district hospitals, and disaster relief setup where power continuity is variable.
Electric & Motorized ICU Beds (DHF Series)
- • Mechanism: Silent linear actuator system with handset control and dedicated nurse Attendant Control Panel (ACP).
- • Safety Features: Lockout key on nurse panel to prevent accidental patient-induced motion, integrated battery backup.
- • Clinical Advantage: Instant cardiac chair positioning, 12°–15° Trendelenburg for hypovolemic shock management.
- • Best Suited For: NABH/JCI accredited multi-specialty ICUs, ventilator patients, and acute post-cardiac surgical care.